
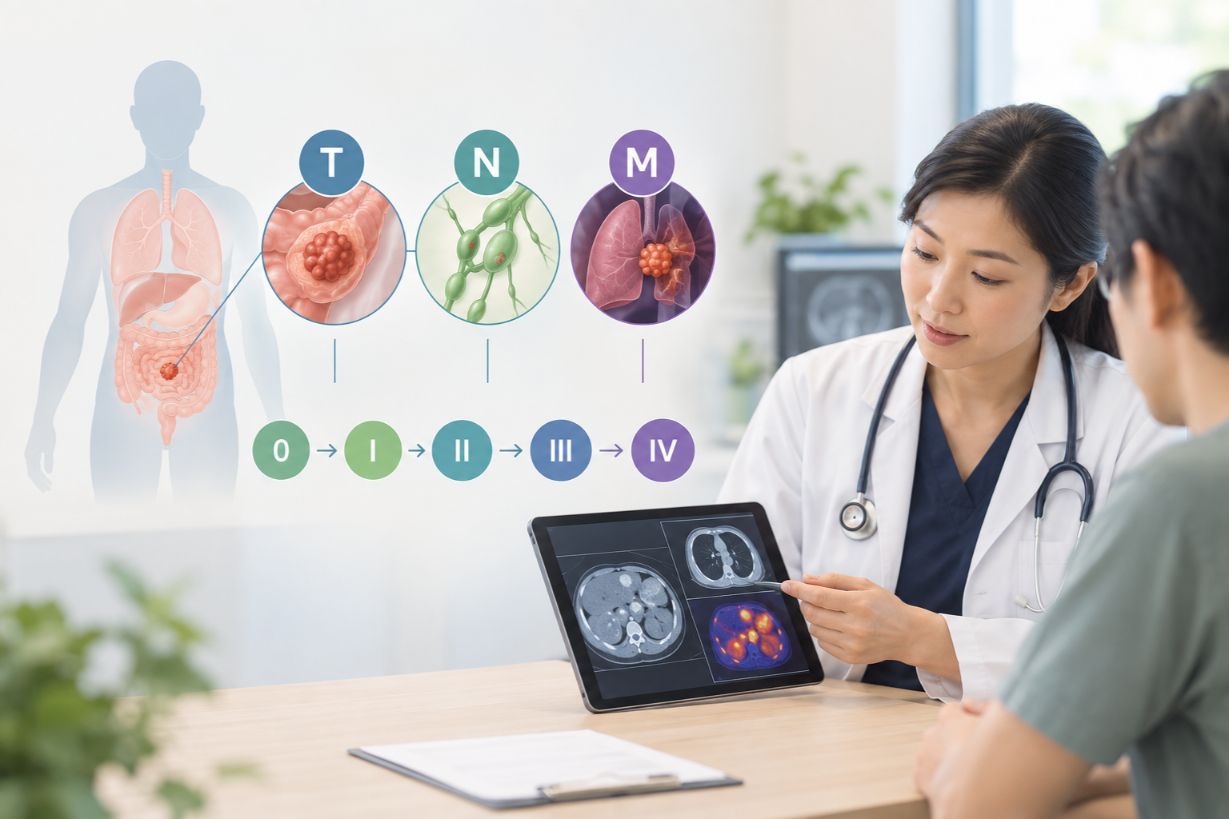
TNM is the most widely used way to describe how far a cancer has grown and spread. T stands for tumour (how large or deep the main tumour is), N for nodes (whether cancer has reached nearby lymph nodes) and M for metastasis (whether it has spread to distant organs). The three scores are combined into an overall stage, usually from 0 to IV, which helps your doctors assess the degree of the spread of the cancer and plan the appropriate treatment.
Key takeaways
- TNM stands for Tumour, Node and Metastasis, and each letter gets a number or letter score.
- The TNM scores combine into a stage group from 0 (very early) to IV (spread to distant parts of the body).
- The same letters mean slightly different things for each cancer type, so a T2 bowel cancer is not measured the same way as a T2 breast cancer.
- Staging uses scans, endoscopy, biopsies and sometimes surgery, and may be updated after the tumour is removed and examined.
- Stage is one factor in treatment planning; tumour grade, cancer type and your overall health also matter.
What does TNM stand for in cancer?
TNM stands for Tumour, Node and Metastasis. It is an international system maintained by the American Joint Committee on Cancer (AJCC) and the Union for International Cancer Control (UICC), and it is used by cancer teams in Singapore and around the world.
Each part answers one question:
- T (tumour): How big is the main tumour, or how deeply has it grown into the organ wall and nearby tissue?
- N (nodes): Has the cancer reached the lymph nodes? Lymph nodes are small bean-shaped glands that filter fluid and are often the first place cancer spreads.
- M (metastasis): Has the cancer spread to distant organs, such as the liver, lungs or bones? Metastasis simply means spread to a distant site.
How do you read T, N and M scores?
Each letter is followed by a number or letter, and higher numbers generally mean a larger tumour or more spread. The table below shows the general pattern.
| Category | Score | What it generally means |
|---|---|---|
| T | TX | The main tumour cannot be assessed |
| T | T0 | No evidence of a main tumour |
| T | Tis | “In situ”: abnormal cells only in the top layer of tissue, not yet invading deeper |
| T | T1 to T4 | Increasing size or depth of growth into the organ and surrounding tissue |
| N | NX | Nearby lymph nodes cannot be assessed |
| N | N0 | No cancer in nearby lymph nodes |
| N | N1 to N3 | Cancer in nearby lymph nodes; higher numbers mean more nodes or nodes further away |
| M | M0 | No distant spread found |
| M | M1 | Cancer has spread to distant organs or distant lymph nodes |
So a report reading “T2 N0 M0” describes a tumour that has grown to a moderate size or depth, with no lymph node involvement and no distant spread. Some cancers also use extra letters, such as T1a or N2b, to give more detail.
For cancers of the digestive tract, T is mainly about depth. The stomach, oesophagus and bowel walls are made of layers, and the T score reflects how many layers the tumour has grown through, rather than its width.
How does TNM turn into a stage from 0 to IV?
Doctors combine the T, N and M scores into a stage group, written in Roman numerals. The rules for combining them are set separately for each cancer type.
| Stage | General meaning |
|---|---|
| Stage 0 | Abnormal cells found only in the lining where they started (in situ) |
| Stage I | Small cancer that has not spread to lymph nodes |
| Stage II | Larger or deeper cancer, sometimes with limited lymph node involvement, depending on cancer type |
| Stage III | Cancer that has grown further and usually involves nearby lymph nodes |
| Stage IV | Cancer that has spread to distant organs (any M1) |
Stages are often split further, for example IIA or IIIB. For some cancers, other factors such as tumour grade or certain blood markers are also built into the stage group.
How is cancer staged?
Staging uses information from several tests put together. For cancers of the stomach, oesophagus and bowel, this commonly includes:
- Biopsy: a small tissue sample, often taken during an endoscopy or colonoscopy, confirms that cancer is present and what type it is.
- CT scan: checks the size of the tumour and looks for spread to lymph nodes, the liver and lungs.
- PET-CT scan: may be used in some cases to look for spread elsewhere in the body.
- Endoscopic ultrasound: an ultrasound probe on an endoscope that measures how deep the tumour goes into the wall, useful for some upper digestive cancers.
- Staging laparoscopy: in selected patients, a keyhole look inside the abdomen to check for small deposits that scans can miss.
You can see how this applies in practice on our pages on the stomach cancer staging assessment and oesophageal cancer surgery.
What is the difference between clinical and pathological stage?
Clinical stage is the estimate made before treatment, based on examination, scans and biopsy. Pathological stage is worked out after surgery, when a pathologist examines the removed tumour and lymph nodes under a microscope.
You may see a small letter in front of the TNM score. A “c” (such as cT2) means clinical stage, and a “p” (such as pT2) means pathological stage. A “y” prefix (such as ypT1) means the stage was assessed after treatment such as chemotherapy given before surgery. The pathological stage can be higher or lower than the clinical one, which is why your team may update your plan after surgery.
Is stage the same as grade?
No. Stage describes how far the cancer has grown and spread. Grade describes how abnormal the cancer cells look under the microscope, which gives a sense of how aggressive or quickly they may grow.
A low-grade cancer has cells that look closer to normal cells. A high-grade cancer has cells that look very abnormal. Both stage and grade are considered, along with the cancer type and your general health, when planning treatment.
Why does cancer stage matter for treatment?
Stage helps your team choose the right treatment and explain what to expect. Earlier-stage cancers of the digestive tract may be treated with surgery alone, sometimes with a minimally invasive (keyhole) approach. More advanced stages may need a combination of chemotherapy, radiotherapy and surgery, planned by a team of specialists.
Stage is a guide, not a prediction for any one person. Two people with the same stage may respond differently to treatment. Our overview of cancer surgery and the types of surgery used explains the options in more detail, including surgery used to help with staging itself.
When to speak to a doctor
If you have been told you have cancer and do not understand your stage, ask your doctor to go through your report with you. Useful questions include: what is my T, N and M score, is this a clinical or pathological stage, and how does it change my treatment options?
If you have symptoms such as a lasting change in bowel habit, blood in the stool, difficulty swallowing, persistent indigestion or unexplained weight loss, see your GP or a polyclinic for assessment. Most of these symptoms have non-cancer causes, but checking early keeps more options open. Our article on colorectal cancer warning signs lists symptoms that warrant a check. For a surgical opinion or a review of your staging results, you can contact KYM Surgery.
Frequently asked questions
Not always. Stage IV means the cancer has spread to distant organs, but treatment can still control the disease for long periods in some people, and for a small number of cancers with limited spread, surgery may still be considered. Your team can explain what applies to your situation.
The original stage at diagnosis stays on record, even if the cancer later grows or responds to treatment. If cancer comes back, doctors may restage it and mark it with an “r” prefix, but they do not rewrite the first stage.
No. Most solid tumours, such as stomach, bowel, oesophageal, breast and lung cancers, use TNM. Blood cancers like leukaemia, lymphomas, many brain tumours and some childhood cancers use their own staging systems.
Before surgery, stage is estimated from scans. After surgery, the pathologist can count the lymph nodes and measure the tumour directly, which gives a more accurate pathological stage. This can move the stage up or down.
It means abnormal cells are found only in the surface layer where they started and have not invaded deeper tissue. It is often described as stage 0 and is usually very treatable.
This article is for general information only and is not a substitute for medical advice. Please consult a qualified doctor for advice specific to your situation.